A 56 year old male presented on 27 Dec 2006 with c/o vague pains all over the body. He gave h/o fever with chills about a week before onset of these symptoms. Clinically there was no significant abnormality and an initial diagnosis of Viral Fever (? Chikungunya) was made. He was treated with Tab paracetamol (acetaminophen) 500 mg tid with Tab B Complex daily.
He came back to us on 16 Jan 2007 with (i) Pain and swelling in the small and medium sized joints, with early morning stiffness (ii) Parasthesiae in the lower limbs (iii) Mild breathlessness.
Clinically: Vitals were within normal limits. There was marked swelling of the Interphalangeal and ankle joints.
Investigations: Hb 12.5 gm%, ESR 10 mm, Total Count: 5000/cumm, P 70, L 27, E 02, M 01, Random Blood Sugar 90 mg%, VDRL - Non Reactor, RA Factor - non reactor
The diagnosis now looked like Sero Negative Polyarthritis.
He was started on Tab Diclofenac 50 mg bid, Tab Folic Acid 5 mg od.
0n 22 Jan 2007 he was reviewed and his condition had worsened - (i) increased pain all over (ii) Unable to walk or lift hands above the head (iii) increasing tremulousness.
Clinically - All joints were swollen and movements of all limbs were sluggish. This prompted me to do a CNS exam:
Power UL - Grade IV, Lower limbs Gd III - IV, Deep Tendon Jerks Bilaterally diminished, absent ankle jerks. Plantars were flexors.
Sensory - Fine touch was absent till mid chest. There was patchy loss of pain and vibration sense over the legs and upper arms.
This got my suspicion up and I thought of an Acute Cervical Cord Lesion.
NIMHANS being the closest and most affordable we sent him there. By the time he reached NIMHANS, about 150 km over bad roads, he had developed acute retention of Urine and needed to be catheterised.
MRI showed:
1. Extruded disc material and superior migration/ Extradural lesion at C5 C6 levels causing focal compression and thinning of cord.
2. Cervical Spondylosis with myelomalacial changes.
Just putting up this as a reminder that what is apparent may not be the actual facet of the illness. We need to keep our eyes and ears open for the most unexpected. After this I did a search using both PubMed and Google Scholar, but really found no such progression described.
Any comments from the Neurologists/Physicians/Neurosurgeons??
Tuesday, February 20, 2007


Diagnostic Conundrum - ? Budd Chiari
A 24 year old lady presented to our centre with c/o vague abdominal pain, acid eructations and poor apetite. She was seen by doctors in Madanapalle and treated with PPIs as well as Antacids.
A G3 P3, 1st child born through LSCS.
O/E: General Exam - was normal.
Abdomen: Tortuous dilated superficial abdominal veins, with hepatic flow. (The pictures below show you the location and size of the veins)


There was a 2 cm soft hepatomegaly, no splenomegaly or free fluid.
USG: Mild to moderate hepatomegaly, abdominal varices, prominent mid hepatic vein with absence of right and left hepatic veins.
Whats the Diagnosis and how will you proceed? Please help????
A G3 P3, 1st child born through LSCS.
O/E: General Exam - was normal.
Abdomen: Tortuous dilated superficial abdominal veins, with hepatic flow. (The pictures below show you the location and size of the veins)


There was a 2 cm soft hepatomegaly, no splenomegaly or free fluid.
USG: Mild to moderate hepatomegaly, abdominal varices, prominent mid hepatic vein with absence of right and left hepatic veins.
Whats the Diagnosis and how will you proceed? Please help????
Tuesday, February 13, 2007
Our First TB Culture
 Hi all
In this not so clear photograph, you can see the yellowish cream colonies of Mycobacterium Tuberculosis, grown in our Microbiology Laboratory.
The patient is in all likelihood a case of MDR TB, due to multiple, ill advised, irregular Anti TB Therapy instituted at various times.
Diagnostic Conundrum (1)

A 26year old male presened to the RHC with a 6 month h/o
(i) Progressive inability to lift both hands baove shoulder
- (ii) Weakness and wasting of shoulder muscles
He denied any h/o substance abuse, trauma, fevers, convulsions, or exposure.
Clinically: Pulse 78/min, BP 110/70 mm Hg. No lymphadenopathy, icterus or pallor.
CNS: Higher mental functions were within normal limits. There were no cranial nerve anomalies. Spine was normal - no deformity, tenderness or gibbus.
Bilateral symmetrical wasting of shoulder muscles (see photo) with clearly defined bony prominences.
Power at shoulder joint: Shoulder shrug V/V, Abduction O/V, Adduction III/V, Extension III/V, Flexion III/V, Ext Rotation III/V. Unable to lift hand over the head but when he moves his upper limb at a rapid pace he is able to lift his hands over the head.
All other muscle groups power was V/V. Deep tendon jerks unaffected.
There was no sensory deficit.
Investigations: Hb 10 gm%, Total and Differential Counts: WNL, ESR 20 mm 1 st hour, Urine analysis : WNL, HIV (Tridot) - ve.
We could not do CPK due to lack of facilities.
SO WHAT's THE DIAGNOSIS? I put it as FASCIO SCAPULO HUMORAL DYSTROPHY or some other Muscular Dystrophy.
The biggest problem is that this young man is the sole earning member of his family, ekeing out a living on daily wages, and as he can not work, or rather no one is willing to give him work because of his disability, he has been reduced to abject poverty. I am trying to raise funds to send him to Bangalore to at least get a diagnosis. Even with a diagnosis, there is really nothing one can do for him, I suppose and that is the saddest part of it all.
Thursday, February 08, 2007
January 2007
The New Year opened with a bang in many ways - what with festivals and patients our cup was rather full.
January is also the month of festivals, with Pongal/ Sankranti being celeberated with great enthusiasm here in the south by one and all, irrespective of caste, creed or religion. This is the harvest festival and it is a very important one. Traditionally a pot of rice, milk and jaggery are cooked together and the pot has to boil over signifying a year full of cheer and bounty ahead. The cattle are all bedecked as they are the ones who actuually provide the work force around here. Tractors still being too expensive and the fact that tractors can not provide milk(!).
So also ID was also celeberated with great fervour. We had to refuse any number of invitations to partake in the feasts as both of us are vegetarian.
Just to see the spirit of the people celeberating these festivals is, as always, an eye opener to me about how people live together in peace and harmony.
January also ushered in the new year and the republic day. We decided to close for these days and fortunately/unfortunately these days happened to fall onour OPD days. Not that any one was cribbing.
Well, started on 03Januray our first working day with a 184 patients. Whew ! at the end of the day Vidya and I were staggering. The relentless pressure kept on and in spite of only 9 OPD days we ended up seeing 1571 patients. January ended with 188 patients and we are desperately hoping for a respite or someone to help us.
We finally also started work on an extension to the building, a waiting room for patients and a water point. I will be publishing these photos soon along with what we plan to do with the extra spaces we have created.
Watch out for Diagnostic Conundrums being published soon.
January is also the month of festivals, with Pongal/ Sankranti being celeberated with great enthusiasm here in the south by one and all, irrespective of caste, creed or religion. This is the harvest festival and it is a very important one. Traditionally a pot of rice, milk and jaggery are cooked together and the pot has to boil over signifying a year full of cheer and bounty ahead. The cattle are all bedecked as they are the ones who actuually provide the work force around here. Tractors still being too expensive and the fact that tractors can not provide milk(!).
So also ID was also celeberated with great fervour. We had to refuse any number of invitations to partake in the feasts as both of us are vegetarian.
Just to see the spirit of the people celeberating these festivals is, as always, an eye opener to me about how people live together in peace and harmony.
January also ushered in the new year and the republic day. We decided to close for these days and fortunately/unfortunately these days happened to fall onour OPD days. Not that any one was cribbing.
Well, started on 03Januray our first working day with a 184 patients. Whew ! at the end of the day Vidya and I were staggering. The relentless pressure kept on and in spite of only 9 OPD days we ended up seeing 1571 patients. January ended with 188 patients and we are desperately hoping for a respite or someone to help us.
We finally also started work on an extension to the building, a waiting room for patients and a water point. I will be publishing these photos soon along with what we plan to do with the extra spaces we have created.
Watch out for Diagnostic Conundrums being published soon.
October to December 2006
Hey Guys forgot to put up the statistics for these months - rather amiss of me. The patient load is never ending and we have had trouble in keeping up with the load.
So here goes:
October 2006: 1036 patients, 63 eye patients, 23 cataracts done at Madanaplle. We worked only three weeks this month before pushing off for a break.
November 2006: Repoened the Health Centre on the 10th of November and in the first week, we did refresher traing for all our staff on basics of health care and management of emergencies. It really paid off because soon after reopening we had a lady who had a convulsion at our door step and the staff were able to handle it without resorting to "nails" etc.
We saw 518 patients, 54 eye patients of which 7 of them were operated for cataracts.
December 2006: Boy, this has been a tough month. 1776 patients blew us away, 82 eye patients and 16 operated. We could have operated more but for a shortage of funds. We raelly are struggling to make both ends meet and are hoping that some of who read this would contribute to our Health Centre.
So here goes:
October 2006: 1036 patients, 63 eye patients, 23 cataracts done at Madanaplle. We worked only three weeks this month before pushing off for a break.
November 2006: Repoened the Health Centre on the 10th of November and in the first week, we did refresher traing for all our staff on basics of health care and management of emergencies. It really paid off because soon after reopening we had a lady who had a convulsion at our door step and the staff were able to handle it without resorting to "nails" etc.
We saw 518 patients, 54 eye patients of which 7 of them were operated for cataracts.
December 2006: Boy, this has been a tough month. 1776 patients blew us away, 82 eye patients and 16 operated. We could have operated more but for a shortage of funds. We raelly are struggling to make both ends meet and are hoping that some of who read this would contribute to our Health Centre.
Thursday, January 11, 2007
November - December 2006
Hi All
Into the new year and may it bring cheer to all the people of the world especially the old and the poor.
The December monsonns have failed us and so we look "forward" to a hot and dusty summer. As it is the experts are proclaiming the year 2007 as the hottest one in history. One hopes that this hot summer along with the El Nino phenomenon does not play havoc with our monsoons. There is barely any water left in our open wells and tanks and soon it will only be a marsh land only to dry out to a hard baked clayey surface.
We had gone on a two week vacation in November and had closed the health centre. After our reopening, the centre continues to be as busy as before. Patients keep pouring in in droves stretching our resources to the limit. It seems almost impossible to keep up ones concentration at the end of the day. Mistakes do happen. At times we are forced to undertreat and call the patient back the next day just for want of time and the fatigue of seeing more than 120 patients of all sorts.
Funds continue to be a problem, though some alumni of the school have promised some money. One hopes that we get some soon.
We are looking for donors as well as any doctor who might be interested in working in a rural setting.
Bye one and all
Into the new year and may it bring cheer to all the people of the world especially the old and the poor.
The December monsonns have failed us and so we look "forward" to a hot and dusty summer. As it is the experts are proclaiming the year 2007 as the hottest one in history. One hopes that this hot summer along with the El Nino phenomenon does not play havoc with our monsoons. There is barely any water left in our open wells and tanks and soon it will only be a marsh land only to dry out to a hard baked clayey surface.
We had gone on a two week vacation in November and had closed the health centre. After our reopening, the centre continues to be as busy as before. Patients keep pouring in in droves stretching our resources to the limit. It seems almost impossible to keep up ones concentration at the end of the day. Mistakes do happen. At times we are forced to undertreat and call the patient back the next day just for want of time and the fatigue of seeing more than 120 patients of all sorts.
Funds continue to be a problem, though some alumni of the school have promised some money. One hopes that we get some soon.
We are looking for donors as well as any doctor who might be interested in working in a rural setting.
Bye one and all
Saturday, December 09, 2006
Musings
They come from far, they come from near, the old and the young, the infirm and the diseased - all seeking succour at the Centre. How many people, how many ailments, all clamouring for help. At times just seeing the mass of huamnity waiting at the doors makes the heart sink. The need to be constantly alert, particularly at the end of a long day, takes its toll. The aged and the poor have their own insecurities, many a time a kind word, a smile is all that it takes to reduce the twin burdens of age as well as poverty - one can do nothing much about either - at best some palliation - some placebos - knowing that these medicines will not harm them.
An old man walks, rather limps in. As one talks with him, I find that he is my age. Relentless poverty, a harsh environment and the daily struggle for livelihood have aged him. Clinically he has moderate to severe osteoarthritis in both the knees - we all know the cause factors - poor nutrition, overuse of joints etc. Anti-inflammatory as well as analgesics will only help him up to a certain point. Then what - knee replacement!!!!
He breaks down, he has a son, who is bright and doing well in school. The boy wants to study further, the father says "who will support the family? I can not work and there needs to be food in the house". There is no answer to this conundrum.
Coming to the health centre is a double whammy - loss of a day's wages (about Rs 50) as well as havng topay for the medicines (Rs 10). How does one recompense that? So many questions at all times. At times I wish I had a million bucks everyday to help out the needy but thats just a dole.
Health can never improve without some improvement in the economic status of the poor. That is a big challenge which faces each and every one of us. The healthy GDP does not reflect in the lives of the poor in this country. Economic policies are possibly skewed. Yes setting up SEZs are good for the country - but why take prime fertile land? Why can not these be set up in arid "unproductive" land?? Not that any land can be considered unproductive take Ralegaon Sidhi as an example.
These are just some thoughts that keep coming up in my mnd. The public forum seems an ideal place in which to share these thoughts.
Bye one and all
Kartik
An old man walks, rather limps in. As one talks with him, I find that he is my age. Relentless poverty, a harsh environment and the daily struggle for livelihood have aged him. Clinically he has moderate to severe osteoarthritis in both the knees - we all know the cause factors - poor nutrition, overuse of joints etc. Anti-inflammatory as well as analgesics will only help him up to a certain point. Then what - knee replacement!!!!
He breaks down, he has a son, who is bright and doing well in school. The boy wants to study further, the father says "who will support the family? I can not work and there needs to be food in the house". There is no answer to this conundrum.
Coming to the health centre is a double whammy - loss of a day's wages (about Rs 50) as well as havng topay for the medicines (Rs 10). How does one recompense that? So many questions at all times. At times I wish I had a million bucks everyday to help out the needy but thats just a dole.
Health can never improve without some improvement in the economic status of the poor. That is a big challenge which faces each and every one of us. The healthy GDP does not reflect in the lives of the poor in this country. Economic policies are possibly skewed. Yes setting up SEZs are good for the country - but why take prime fertile land? Why can not these be set up in arid "unproductive" land?? Not that any land can be considered unproductive take Ralegaon Sidhi as an example.
These are just some thoughts that keep coming up in my mnd. The public forum seems an ideal place in which to share these thoughts.
Bye one and all
Kartik
Sunday, December 03, 2006
Venkataramanama - An Update

What a smile - Venkataramanama after six months of Anti Tuberculosis Treatment. If you all remember, she had Disseminated TB necessitating admission in St Johns Medical College at Bangalore. (see post "Case of the month - June 2006)
She has been a regular visitor the Health Centre and her smiles seem to light up the the room. She comes from a little hamlet about 30 km away, changing three buses on the way. Quite remarkable considering that she is only 10 years old and barely literate. Her parents are too poor to accompany her all the way to the health centre and therefore our instructions to her have to be very simple and straightforward.
One of our most cooperative patients, she has helped us learn about fortitude and courage.
Saturday, November 25, 2006
Sunita - A Girl Child

Sunita is a 11 year old girl studying in our Rural School. An alert teacher noted that she was having difficulty concentrating, falling off to sleep and was not eating properly. The Teacher spent some time with her parents and found that they had also noted the same problems. So he sent her to us.
After examining her, we found that she was quite severely malnourished - Grade III - the cause - Worms and the misfortune of being born a girl!
Treatment was simple, but the time spent with the parents counselling them was very productive.
The teacher is very happy with Sunita's progress and he has told me that she is now active in class, interested in her subjects, active and mixing well with all the others.
The teamwork and close cooperation between the health and education centres has been able to help out this poor girl child.
Wednesday, October 18, 2006
September 2006
The merry month of September has gone past in a whizz leaving us all quite breatless and tired. The sheer numbers are quite overwhelming:
- 1729 patients seen in the OPD
- 26 Cataracts operated in Madanapalle - "Words can not express our gratitude to Dr TN Krishna Reddy and Dr Shobha Naveen, who operate on our patients at minimum cost."
- 2 Deliveries: Thanks to Dr Asha Neeraja at Madanapalle - one of whom had Pregnancy Induced Hypertension, Intra Uterine Growth Retardation as well as prematurity - the mother and kid are doing fine - that both survived is a testament to the skills of the doctor as well as the nursing staff and to top it all guess how much it cost LSCS + Incubator care = Rs 6700/- only. Can you believe it - who says that quality health care can not be provided at low cost.
The end of September was also a time to reflect and take stock of what had transpired in the past 6 months - a 6 monthly review of sorts - while our patient numbers are impressive (7202 patients from April, 113 Cataracts operated upon, 8 deliveries, including 2 LSCS, no Infant or Maternal deaths), the fact is that we are struggling financially.
A 100,000 rupees in the red, god knows where the money is going to come from. Also we desperately need money to build a waiting room for the patients - the trees providing the only cover at present. That is going to cost us another couple of lakhs. Anyone willing to help???
Bye one and all
Kartik
Thursday, September 07, 2006
August 2006
Another month goes by and one is confronted with patients of all types, some near the end of their thether, having gone from pillar to post seeking succour,mostly in vain. In spite of having been in this profession for more than 20 years, disease and death are not easy to get used to.
The poor flock to our centre, seeking professional advise and possibly the right kind of treatment - Iatrogenic Poverty is a major issue with ruthless practitioners out to fleece the poor, ignorant public of what little money they have. So also inappropriate therapy, treatment modalaties, unnecessary surgeries all in the guise of medicine and serving the sick - Whither art thou Hippocrates???
Well the health centre goes on - We saw 1441 patients, did 17 cataract surgeries and 2 Dacryocystectomies and delivered 2 babies both above 2.5 kg. Considering that we started with 1.8 kg, this is quite an achievement.
In the adjoining phot you can see a child being nebulised in our centre. I am sure that the paediatricians would say - it is not the mostideal of circumstances - I agree - but something better than nothing.
Anyway, this child went to a "paediatrician" with c/o fever of less than 2 days duration. No investigations were done and the "good doctor" started him on - hold your breath - Inj Amikacin, Inj Cefatoxime and Inj Metrogyl - wow - should take care of everything!!!!
Well the child did not recover and having spent a couple of thousand rupees and in debt with an interest rate of 4% pm (48% pa),they came to us. Examined the kid and found Heaptosplenomegaly with a Hb 7 gm%, Pl Vivax, TC 6200/cumm, S Bilirubin 2.8 mg%, with conjugated hyperbilirubinaemia - Simple - Treat with Chloroquin 10 mg/kg and child was afebrile in a day and was doing well.
Unfortunately Child developed Hyperactive Airway Disease with LRTI and is now on treatment for the same. Am sure that the child will recover at the soonest.
Take care all and see you soon
The poor flock to our centre, seeking professional advise and possibly the right kind of treatment - Iatrogenic Poverty is a major issue with ruthless practitioners out to fleece the poor, ignorant public of what little money they have. So also inappropriate therapy, treatment modalaties, unnecessary surgeries all in the guise of medicine and serving the sick - Whither art thou Hippocrates???
Well the health centre goes on - We saw 1441 patients, did 17 cataract surgeries and 2 Dacryocystectomies and delivered 2 babies both above 2.5 kg. Considering that we started with 1.8 kg, this is quite an achievement.
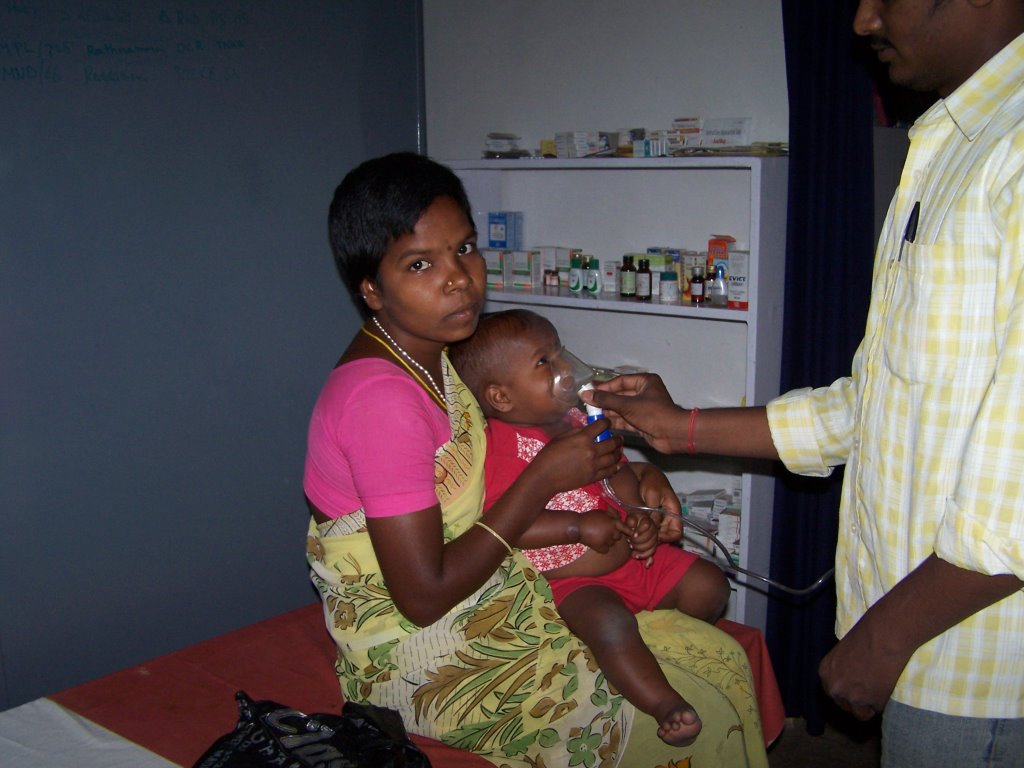
In the adjoining phot you can see a child being nebulised in our centre. I am sure that the paediatricians would say - it is not the mostideal of circumstances - I agree - but something better than nothing.
Anyway, this child went to a "paediatrician" with c/o fever of less than 2 days duration. No investigations were done and the "good doctor" started him on - hold your breath - Inj Amikacin, Inj Cefatoxime and Inj Metrogyl - wow - should take care of everything!!!!
Well the child did not recover and having spent a couple of thousand rupees and in debt with an interest rate of 4% pm (48% pa),they came to us. Examined the kid and found Heaptosplenomegaly with a Hb 7 gm%, Pl Vivax, TC 6200/cumm, S Bilirubin 2.8 mg%, with conjugated hyperbilirubinaemia - Simple - Treat with Chloroquin 10 mg/kg and child was afebrile in a day and was doing well.
Unfortunately Child developed Hyperactive Airway Disease with LRTI and is now on treatment for the same. Am sure that the child will recover at the soonest.
Take care all and see you soon
Thursday, August 17, 2006
July 2006
The busy month of July came to an end and boy did we struggle.
1551 patients - in 12 working days - work that out!
Ouch just looking back at it makes me dizzy.
32 Cataracts and operated upon in July - that itself is some sort of a record.
Of course we are desperately short of Funds - Please help
kartik
1551 patients - in 12 working days - work that out!
Ouch just looking back at it makes me dizzy.
32 Cataracts and operated upon in July - that itself is some sort of a record.
Of course we are desperately short of Funds - Please help
kartik
Tuesday, July 18, 2006
What's the Diagnosis?
Hanumanthu 45/M
Presented with H/O
Presented with H/O
- Increasing difficulty in walking: 4 days
- Pain in the joints with associated swelling: 4 days
On further questioning:
- Progressive loss of weight: 4 months
- Anorexia: 4 months
- No h/o - Nausea/Vomiting/Haematemesis/Cough/Fever/Unusual swellings/Non healing ulcers.
Examination:
- Weight 39 kg Height 170 cm, Afebrile
- Pallor ++, Icterus +/-, Bilateral pitting oedema over the ankles, No lymphadenopathy/ Clubbing/ Skin changes
- Pulse 110/minute, BP 110/70 mm Hg
Systems:
ABDOMEN:
- Thin, Liver palpable 2.0 cm
- Spleen NP
- No evidence of free fluid
CNS:
- Gd III/V power both Upper as well as lower limbs
- DTJ: Sluggish
- Plantars: Flexor
CVS/RS: NAD
What's the suspicion?
How will you proceed - remember this is a primary care setting.
PART 2
Investigations:
Hb: 9.5 gm%, TC 6000/cumm, P 88 (Neutrophils show toxic granulations) L12, RBS 115 mg%
Urine: Albumin +++, Pus cells Numerous, RBCs 1-2, Epith Cells 2-4, Ca Oxalate crystals 8 - 10
X-Ray Chest PA: Hilar flare ? Para hilar and mediastinal nodes enlarged
The following tests ordered LFT , Blood Urea, Creatinine, HIV and HBSAg
Wow - now what - the picture gets more and more confusing:
So when in doubt - Started Cap Amoxycillin 500 mg tid along with B-complex
Part 3
The patient comes back after a couple of days:
No change except that the joint pains have reduced:
Investigations:
Total Bilirubin: 2.15 mg%, Direct 1.55, Indirect 0.60 ???
SGOT: 113 u/L, SGPT 24 u/L, Alk PO4ase 134 IU/L
Total Proteins 5.6 gm%, Albumin 3.4, Globulin 2.2, A:G Ratio 1:1.5
Urea 15 mg%, Creatinine 0.9%
HIV (Tridot) -ve HBSAg (Hepacard)-ve
On the basis of this a presumptive diagnosis of CA Head Pancreas was made - on clinical grounds
USG: Hepatomegaly with fatty changes, Large cystic lesion of Head of pancreas (?Infective etiology), Cystic lesion Anterior to Aorta - possibility of necrotic lymph node/Aneurysm
NOW WHAT - Patient has disappeared and we are trying to trace him.
Are we looking at a TB etiology???
Answers please
Tuesday, July 04, 2006
Cases of the Month - June 2006
Naresh, aged 10, presented to us with right sided pain abdomen and

severe respiratory distress. Clinically he was febrile 40 C, tachypnoeic (RR > 45/min), BP 90/60 and falling, Abdomen was tense with guarding in the Rght upper quadrant, Trachea shifted to left with absent movements and breath sounds in the Right Hemithorax. An erect plain film confirmed the clinical findings.
We suspected an Amoebic Liver Abscess which had burst upwards. We stabilised him with IV fluids, IV antibiotics and transferred him immediately to St Johns Medical College, where > 2.7 litres of pus was drained. A pigtailed catheter drained for a week.
He is now better though there is a residue of Right Lower Lobe atelectatsis, which should improve with chest physiotherapy.
 Venkataramanama, aged 9 presented to us with progressive loss of weight, anorexia, nausea, early fullness, easy fatiguability and multiple lymph nodes (axillary as well as cervical). Clinically she was febrile 38 C, marked pallor, firm, tender nodes 1.5 x 2 cm size. Her abdominal findings were classical - Doughy abdomen, with dull note on percussion, diminished bowel sounds.
Investigations: Hb 6 gm%, ESR 110 mm 1 st hour, X-Ray showed hilar flare and enlarged para hilar nodes. Weight 12 kg
This was enough to come to a diagnosis of (1) Disemminated TB (2) Grade 3 Malnutrition.
We have started her on Anti Tuberculous Treatment with adjunct steroids, nutritional supplements (basically stuff like jaggery, ragi, fenugreek, spinach, drumstick leaves, sprouts) and am happy to report that she is doing well.
She is now 4 weeks into the treatment and her Hb is 9 gm%, apetite has markedly improved, weight has gone up to 15 kg.
We are hopeful that she will recover well enough in due course.
Watch this space for progress reports.

severe respiratory distress. Clinically he was febrile 40 C, tachypnoeic (RR > 45/min), BP 90/60 and falling, Abdomen was tense with guarding in the Rght upper quadrant, Trachea shifted to left with absent movements and breath sounds in the Right Hemithorax. An erect plain film confirmed the clinical findings.
We suspected an Amoebic Liver Abscess which had burst upwards. We stabilised him with IV fluids, IV antibiotics and transferred him immediately to St Johns Medical College, where > 2.7 litres of pus was drained. A pigtailed catheter drained for a week.
He is now better though there is a residue of Right Lower Lobe atelectatsis, which should improve with chest physiotherapy.
 Venkataramanama, aged 9 presented to us with progressive loss of weight, anorexia, nausea, early fullness, easy fatiguability and multiple lymph nodes (axillary as well as cervical). Clinically she was febrile 38 C, marked pallor, firm, tender nodes 1.5 x 2 cm size. Her abdominal findings were classical - Doughy abdomen, with dull note on percussion, diminished bowel sounds.
Investigations: Hb 6 gm%, ESR 110 mm 1 st hour, X-Ray showed hilar flare and enlarged para hilar nodes. Weight 12 kg
This was enough to come to a diagnosis of (1) Disemminated TB (2) Grade 3 Malnutrition.
We have started her on Anti Tuberculous Treatment with adjunct steroids, nutritional supplements (basically stuff like jaggery, ragi, fenugreek, spinach, drumstick leaves, sprouts) and am happy to report that she is doing well.
She is now 4 weeks into the treatment and her Hb is 9 gm%, apetite has markedly improved, weight has gone up to 15 kg.
We are hopeful that she will recover well enough in due course.
Watch this space for progress reports.
April - June 2006
Hi all
Am back after a long time.
As promised here is a monthly update on the Health Centre Activities.
We had closed for a much needed vaction from Mid April - Mid May and now we are back in TOP GEAR - cruising along seeing upwards of a 100 patients in the OPD.
We also had a number of unusual as well as interesting cases over the last few weeks. Will be putting these up with pictures in the next couple of days.
Hey guys we are hard up here - ANY HELP????
Kartik
Am back after a long time.
As promised here is a monthly update on the Health Centre Activities.
We had closed for a much needed vaction from Mid April - Mid May and now we are back in TOP GEAR - cruising along seeing upwards of a 100 patients in the OPD.
We also had a number of unusual as well as interesting cases over the last few weeks. Will be putting these up with pictures in the next couple of days.
Hey guys we are hard up here - ANY HELP????
Kartik
Wednesday, May 31, 2006
A RARE CASE OF TUBERCULOSIS

Khadarvalli - 17 years presented to us with multiple sub cutaneous abscesses of 01 month duration. Mnay of these abscesses had been repeatedly drained at private nursing homes in Madanapalle - Guess what - none of the aspirates or fluid was ever sent for pathological examination.
We suspected Cutaneous Tuberculosis
and found AFB in the aspirate. St Johns Medical College further confirmed the Diagnosis and after surgery to drain all abscesses he was put on Cat I treatment.
Suffice to say that he is doing very well.
SIDDAMMA - Mitral Valve Replacement

Siddamma - Age 15 years - was suffering from Rheumatic Heart Disease, Mitral Regurgitation and Stenosis. She was under medical management for 5 years.
However she progressively developed Cardiac Failure and a superadded Fungal Infection of the Lungs.
She was admitted at NARAYANA HRUDAYALAYA in Bangalore where her condition was stabilised and successfully operated.
She is now doing well. We wish to thank all those donors who helped in her surgery.
Sunday, May 28, 2006
List of Patients Treated at Secondary/Tertiary Centres
1
Chandrakala Bronchopneumonia Amrutha Hospital
2
Amrutha ANC - Delivery Usha Speciality
3
Redappa C TB Abdomen Popular Nursing Home
4
Adilakshmi Vaginal Hysterectomy Usha Speciality
5
Vanisree Parietal Wall abscess Popular Nursing Home
6
Vasantha PIH & Ecclampsia Usha Speciality
7
Varshita Congenital Cataract (optd) Satya Eye Hospital
8
Kanakamma ANC - LSCS Usha Speciality
9
Mehaboob Bee RHD, MS, SVTs Sri Venkateswara Institute Medical Sciences
10
Lakshmamma Dacryocystectomy Satya Eye Hospital
11
Jaithumbee Iridectomy Satya Eye Hospital
12
K Chandra Thyrotoxicosis St Johns Medical College Hospital
SJMCH
13
Masthan Bee TB Lymphadenitis Popular Nursing Home
14
Ademma Left Ovarian Mass + Hysterectomy
Usha Speciality
15
Ramanaiah Paraplegia,Bed Sores, Multi SustemFailure
Popular Nursing Home
16
Syamala Congenital heart Disease
SJMCH
17
Narasimhulu Multiple Perianal Abscess Popular Nursing Home
18
Varalakshmi Chorio Carcinoma SJMCH
19
Bhavani HIV + Lactic acidosis Baptist Hospital
20
E Subbi Reddy TB Lymphadenitis Popular Nursing Home
21
Amravathi Lumbar Canal Stenosis Saptagiri Scans
22
Savithramma Fever MLL
23
Shashikumar Appendicectomy Popular Nursing Home
24
Abilash Hyperactive Airway Disease Amrutha Hospital
SJMCH (2 times)
25
Deekshita Labial Lipoma & Ectopic Anus
SVRR (Tirupati)
26
Baby Hyperactive Airway Disease Amrutha Hospital
27
Jayamma Acoustic Schwanomma SVIMS
28
Anwar Basha TB Abdomen Popular Nursing Home
29
Anil HIV +ve AMC
30
Jabeena Sultana ANC - Delivery Usha Speciality
31
Nagamani HIV +ve SJMCH
32
Sudarshan TB Lymphadenitis Popular Nursing Home
33
Abilash Bronchopneumonia Amrutha Hospital
34
Tejashree Bronchopneumonia Amrutha Hospital
35
Beebeejan Oral Submucosal Fibrosi KMIO
36
Krishnappa Osteomyelitis SILOAM Orthopaedic
37
Manjunath Achondroplastic Dwarf SJMCH
38
Mangamma Bronchiectasis - Lobectomy SJMCH
39
Ganesh P Hyperactive Airway Disease + Bronchopneumonia
SJMCH
40
Anasuya Abdominal TB SJMCH
41
Lakshmaiah IHD + HTN + DM SJMCH
42
Nagamani PUO & HIV SJMCH
43
Jayachandra TB Meningitis SJMCH
44
Nagendra Global Development Decay & Left Eye Catatct (IOL)
SJMCH
45
Abilash Hyperactive Airway Disease + Bronchopneumonia
SJMCH
46
Venkataramana Bronchiectasis + Stevens Johnson
SJMCH
47
Dhanalakshmi Puerperal Sepsis & Peritonitis
SJMCH
48
Bhudevi SLE, Auto Immune Hepatitis
SJMCH
49
Gangabhavani HIV + Lactic acidosis Baptist Hospital
50
Thimmamma Seizure Disorder Apollo Aragonda
51
Ashrafunissa Mullerian Anomaly - Vaginal Agenesis
Sundaram Medical
52
Narsimha Reddy Thyroidectomy Popular Nursing Home
53
Siddamma RHD, MR, CCF - MVR (optd)
Narayana Hrudyalaya
54
Muniyamma PUO RVS
55
Deepak Kumar # Left arm SILOAM Orthopaedic
56
Krishnappa Viral Hepatitis RVS
57
Reddamma Ca Breast Cancer Institute, Chennai
58
Venkatappa Naidu PIVD Lv4 - Sv2 with Neuro deficit
Saptagiri Scans
59
Saroja Ca Ovary Cancer Institute, Chennai
60
B Narasimhulu CA Larynx KMIO
61
T Haritha Cerebral Palsy SJMCH
62
Khadarvalli Multiple TB Abscesses SJMCH
63
Narasamma Incisional Hernia Repair Popular Nursing Home
64
Chandrasekhara Sero -ve arthritis, DM (II) SJMCH
65
Thayaramma Idiopathic Thrombocytopenic Purpura
SJMCH
66
Abhilash Hyperactive Airway Disease SJMCH
67
Susheela ANC-LSCS Usha Speciality
68
Susheela AN C Usha Speciality
69
Raziya ANC Usha Speciality
70
K Basiri Severe Rheumatoid Arthritis SJMCH
71
G Abeda PIVD LV4-5 SJMCH
72
Subhan Basha Bronchiolitis with Hyperactive Airway Disease
Amrutha Hospital
73
S Nouzia DM(II) with Superadded infection
Popular Nursing Home
74
Bharati FB Oesophagus Satya Sai clinic
Chandrakala Bronchopneumonia Amrutha Hospital
2
Amrutha ANC - Delivery Usha Speciality
3
Redappa C TB Abdomen Popular Nursing Home
4
Adilakshmi Vaginal Hysterectomy Usha Speciality
5
Vanisree Parietal Wall abscess Popular Nursing Home
6
Vasantha PIH & Ecclampsia Usha Speciality
7
Varshita Congenital Cataract (optd) Satya Eye Hospital
8
Kanakamma ANC - LSCS Usha Speciality
9
Mehaboob Bee RHD, MS, SVTs Sri Venkateswara Institute Medical Sciences
10
Lakshmamma Dacryocystectomy Satya Eye Hospital
11
Jaithumbee Iridectomy Satya Eye Hospital
12
K Chandra Thyrotoxicosis St Johns Medical College Hospital
SJMCH
13
Masthan Bee TB Lymphadenitis Popular Nursing Home
14
Ademma Left Ovarian Mass + Hysterectomy
Usha Speciality
15
Ramanaiah Paraplegia,Bed Sores, Multi SustemFailure
Popular Nursing Home
16
Syamala Congenital heart Disease
SJMCH
17
Narasimhulu Multiple Perianal Abscess Popular Nursing Home
18
Varalakshmi Chorio Carcinoma SJMCH
19
Bhavani HIV + Lactic acidosis Baptist Hospital
20
E Subbi Reddy TB Lymphadenitis Popular Nursing Home
21
Amravathi Lumbar Canal Stenosis Saptagiri Scans
22
Savithramma Fever MLL
23
Shashikumar Appendicectomy Popular Nursing Home
24
Abilash Hyperactive Airway Disease Amrutha Hospital
SJMCH (2 times)
25
Deekshita Labial Lipoma & Ectopic Anus
SVRR (Tirupati)
26
Baby Hyperactive Airway Disease Amrutha Hospital
27
Jayamma Acoustic Schwanomma SVIMS
28
Anwar Basha TB Abdomen Popular Nursing Home
29
Anil HIV +ve AMC
30
Jabeena Sultana ANC - Delivery Usha Speciality
31
Nagamani HIV +ve SJMCH
32
Sudarshan TB Lymphadenitis Popular Nursing Home
33
Abilash Bronchopneumonia Amrutha Hospital
34
Tejashree Bronchopneumonia Amrutha Hospital
35
Beebeejan Oral Submucosal Fibrosi KMIO
36
Krishnappa Osteomyelitis SILOAM Orthopaedic
37
Manjunath Achondroplastic Dwarf SJMCH
38
Mangamma Bronchiectasis - Lobectomy SJMCH
39
Ganesh P Hyperactive Airway Disease + Bronchopneumonia
SJMCH
40
Anasuya Abdominal TB SJMCH
41
Lakshmaiah IHD + HTN + DM SJMCH
42
Nagamani PUO & HIV SJMCH
43
Jayachandra TB Meningitis SJMCH
44
Nagendra Global Development Decay & Left Eye Catatct (IOL)
SJMCH
45
Abilash Hyperactive Airway Disease + Bronchopneumonia
SJMCH
46
Venkataramana Bronchiectasis + Stevens Johnson
SJMCH
47
Dhanalakshmi Puerperal Sepsis & Peritonitis
SJMCH
48
Bhudevi SLE, Auto Immune Hepatitis
SJMCH
49
Gangabhavani HIV + Lactic acidosis Baptist Hospital
50
Thimmamma Seizure Disorder Apollo Aragonda
51
Ashrafunissa Mullerian Anomaly - Vaginal Agenesis
Sundaram Medical
52
Narsimha Reddy Thyroidectomy Popular Nursing Home
53
Siddamma RHD, MR, CCF - MVR (optd)
Narayana Hrudyalaya
54
Muniyamma PUO RVS
55
Deepak Kumar # Left arm SILOAM Orthopaedic
56
Krishnappa Viral Hepatitis RVS
57
Reddamma Ca Breast Cancer Institute, Chennai
58
Venkatappa Naidu PIVD Lv4 - Sv2 with Neuro deficit
Saptagiri Scans
59
Saroja Ca Ovary Cancer Institute, Chennai
60
B Narasimhulu CA Larynx KMIO
61
T Haritha Cerebral Palsy SJMCH
62
Khadarvalli Multiple TB Abscesses SJMCH
63
Narasamma Incisional Hernia Repair Popular Nursing Home
64
Chandrasekhara Sero -ve arthritis, DM (II) SJMCH
65
Thayaramma Idiopathic Thrombocytopenic Purpura
SJMCH
66
Abhilash Hyperactive Airway Disease SJMCH
67
Susheela ANC-LSCS Usha Speciality
68
Susheela AN C Usha Speciality
69
Raziya ANC Usha Speciality
70
K Basiri Severe Rheumatoid Arthritis SJMCH
71
G Abeda PIVD LV4-5 SJMCH
72
Subhan Basha Bronchiolitis with Hyperactive Airway Disease
Amrutha Hospital
73
S Nouzia DM(II) with Superadded infection
Popular Nursing Home
74
Bharati FB Oesophagus Satya Sai clinic
ANNUAL REPORT - RVRHC
RISHI VALLEY RURAL HEALTH CENTRE
KRISHNAMURTI FOUNDATION INDIA
ANNUAL REPORT 2005 - 06
This year past, saw an exponential growth in the number of patients seen at the Health Centre. From 7400 to 11400 was an unanticipated increase, which, stretched our resources, human, financial as well as psychological to almost breaking point.
It is never easy working day in and out with the poor. People pour into the centre seeking succour for their illnesses. More and more complex diseases, long standing conditions – crippling them, drive the poor into deeper debt. Most times we arrive at a working diagnosis- THEN WHAT? - The levels of poverty in our country are frightening, many cannot even afford a bus fare of Rs 50/- which will get them to Bangalore and a tertiary care centre, forget about meeting costs of investigations and treatment.
One wonders what will happen to the Rural Poor in this age of globalisation, privatisation and exploitation.
OUTPATIENT
Total 11532
Adults 10367
Children 1165
2003-04 6351
2004-05 7481
2005-06 11 532
KRISHNAMURTI FOUNDATION INDIA
ANNUAL REPORT 2005 - 06
This year past, saw an exponential growth in the number of patients seen at the Health Centre. From 7400 to 11400 was an unanticipated increase, which, stretched our resources, human, financial as well as psychological to almost breaking point.
It is never easy working day in and out with the poor. People pour into the centre seeking succour for their illnesses. More and more complex diseases, long standing conditions – crippling them, drive the poor into deeper debt. Most times we arrive at a working diagnosis- THEN WHAT? - The levels of poverty in our country are frightening, many cannot even afford a bus fare of Rs 50/- which will get them to Bangalore and a tertiary care centre, forget about meeting costs of investigations and treatment.
One wonders what will happen to the Rural Poor in this age of globalisation, privatisation and exploitation.
OUTPATIENT
Total 11532
Adults 10367
Children 1165
2003-04 6351
2004-05 7481
2005-06 11 532
The centre saw 11532 patients as compared to 7481 in the year 2004-05 and 6351 in the previous year. This increase in 4000 patients was unprecedented. We found that affordability and quality of service rendered were the two most important components in the decision amongst patients to come to the health centre.
The Manmohini Kaul Charitable Medical trust partly funds the subsidy on treatment for patients.
EYE CARE
The programme went forward another step when we were designated a Vision Care Centre by LV Prasad Eye Institute of Hyderabad. A Humphrey’s Frequency Doubling Test Instrument to measure visual fields was installed in November 2005. It has proved a boon for the early diagnosis of field defects, particularly those caused due to Glaucoma.
Patients 960
Cataracts 142
Other surgeries 10
Glaucoma 28
142 cataracts, 6 Dacryocystectomies and 4 Iridectomies were done at subsidised rates to the poor. In addition 28 patients with incipient Glaucoma were picked up thanks to the FDT instrument. I am glad to report that all patients are doing well.
The Manmohini Kaul Charitable Medical trust partly funds the subsidy on treatment for patients.
EYE CARE
The programme went forward another step when we were designated a Vision Care Centre by LV Prasad Eye Institute of Hyderabad. A Humphrey’s Frequency Doubling Test Instrument to measure visual fields was installed in November 2005. It has proved a boon for the early diagnosis of field defects, particularly those caused due to Glaucoma.
Patients 960
Cataracts 142
Other surgeries 10
Glaucoma 28
142 cataracts, 6 Dacryocystectomies and 4 Iridectomies were done at subsidised rates to the poor. In addition 28 patients with incipient Glaucoma were picked up thanks to the FDT instrument. I am glad to report that all patients are doing well.
AGAMA India partly supports this programme.
SILOAM eye hospital, a branch of LV Prasad Eye Institute, in Madanapalle, has started doing Cataract Surgeries at a nominal cost for our patients. This is in addition to those surgeries being done at a subsidised rate in Satya Eye Hospital, Madanapalle by an ex-parent of the school.
But as with any of our programme, lack of adequate funding remains the biggest constraint.
TUBERCULOSIS PROGRAMME
Total 87
New 68
Old (contd) 19
Sputum + (new) 30
Extra Pulmonary 12
Completed 31
RNTCP 31
Ongoing 12
Died 2
Default 2
The programme continues to be partly funded by the SIDVIM trust. The linkage with the RNTCP has proved to be beneficial, with a number of patients benefiting from access to Government supplied free medicines. Our laboratory has been recognised as a DESIGNATED MICROSCOPY CENTRE under the RNTCP.
What is worrying, however, is the growing incidence of HIV positivity amongst our patients. SIX of our TB patients were found to be HIV positive, one dying within a month of starting treatment. Providing Anti retro viral agents remains a pipe dream. Most of our effort is directed at counselling, the affected person as well as the family members in accepting the disease.
ANTENATAL PROGRAMME
(2005)
Total 30
Home 11
Hospital normal 5
Hospital LSCS 3
Lost to follow up 11
The ante – natal programme continues doing well. There is a greater awareness amongst pregnant women on the need for regular ante natal checks. The lost to follow up is probably because of a number of home deliveries which do not get reported, in spite of our best efforts.
An increasing number of women with multiple pregnancy losses, Bad obstetric history, are accessing our centre for the following reasons (i) comprehensive work up (ii) personalised guidance and counselling, (iii) close monitoring of the ongoing pregnancy (iv) liaison with Fetal Care Research Centre, Chennai and (v) support of a committed Obstetrician (Usha Speciality Hospital) at Madanapalle.
The data for the 4 years of the programme is given below:
Home Hospital normal Hospital LSCS Lost to follow up
2002 4 4 1 5
2003 11 3 4 8
2004 6 6 3 4
2005 11 5 3 11
2006 1 1 -
COMMUNITY DIAGNOSTIC CENTRE
Laboratory 2620
Microbiology 81
X-Ray 438
SILOAM eye hospital, a branch of LV Prasad Eye Institute, in Madanapalle, has started doing Cataract Surgeries at a nominal cost for our patients. This is in addition to those surgeries being done at a subsidised rate in Satya Eye Hospital, Madanapalle by an ex-parent of the school.
But as with any of our programme, lack of adequate funding remains the biggest constraint.
TUBERCULOSIS PROGRAMME
Total 87
New 68
Old (contd) 19
Sputum + (new) 30
Extra Pulmonary 12
Completed 31
RNTCP 31
Ongoing 12
Died 2
Default 2
The programme continues to be partly funded by the SIDVIM trust. The linkage with the RNTCP has proved to be beneficial, with a number of patients benefiting from access to Government supplied free medicines. Our laboratory has been recognised as a DESIGNATED MICROSCOPY CENTRE under the RNTCP.
What is worrying, however, is the growing incidence of HIV positivity amongst our patients. SIX of our TB patients were found to be HIV positive, one dying within a month of starting treatment. Providing Anti retro viral agents remains a pipe dream. Most of our effort is directed at counselling, the affected person as well as the family members in accepting the disease.
ANTENATAL PROGRAMME
(2005)
Total 30
Home 11
Hospital normal 5
Hospital LSCS 3
Lost to follow up 11
The ante – natal programme continues doing well. There is a greater awareness amongst pregnant women on the need for regular ante natal checks. The lost to follow up is probably because of a number of home deliveries which do not get reported, in spite of our best efforts.
An increasing number of women with multiple pregnancy losses, Bad obstetric history, are accessing our centre for the following reasons (i) comprehensive work up (ii) personalised guidance and counselling, (iii) close monitoring of the ongoing pregnancy (iv) liaison with Fetal Care Research Centre, Chennai and (v) support of a committed Obstetrician (Usha Speciality Hospital) at Madanapalle.
The data for the 4 years of the programme is given below:
Home Hospital normal Hospital LSCS Lost to follow up
2002 4 4 1 5
2003 11 3 4 8
2004 6 6 3 4
2005 11 5 3 11
2006 1 1 -
COMMUNITY DIAGNOSTIC CENTRE
Laboratory 2620
Microbiology 81
X-Ray 438
The Community Diagnostic Centre has more than proved its usefulness to us. Not only does the centre cater to the constantly growing needs of the Health Centre, but it also provides diagnostic services to the children of the school. The charges are nominal, covering the cost of chemicals as well as salaries and maintenance. Hence, patients are able to afford the cost of investigations done here.
ULTRASOUND
On 16th Feb 2006, the 2nd anniversary of Dr V Ramamurthy’s demise, his family and friends presented the Health Centre with an Ultrasound. Both of us are feeling our way into this new area and will start using it once training and licensing procedures are completed. We are sure that this machine will prove to be of a great benefit to us.
CAMPS
On 16th Feb, 2006 MMKCMT conducted a Paediatric Camp at the RHC. About 40 children benefited from the services of the visiting paediatrician.
33 patients with eye ailments were seen and 10 of them operated for Cataracts.
Vascular Diseases Project
With an aim at finding out the incidence/prevalence of Hypertension, Diabetes and IHD amongst the rural poor, the Health centre in collaboration with Monash University of Australia, has just started a one year epidemiological survey, covering a population of 5000.
A Closing Message
We would like to take this opportunity to thank one and all for their support to the Rural Health Centre.
A full list of patients who have been treated at Tertiary Care Centres will be put up on the blogspot at the soonest.
We look forward to your continuing support in the years to come. Please look at www.rvrhc.blogspot.com for our funding requirements.
Kartik and Kamakshi
April 2006
rvsrhc@yahoo.co.in www.rvrhc.blogspot.com www.rishivalley.org
(08571) 280573/280850/280622/280582
ULTRASOUND
On 16th Feb 2006, the 2nd anniversary of Dr V Ramamurthy’s demise, his family and friends presented the Health Centre with an Ultrasound. Both of us are feeling our way into this new area and will start using it once training and licensing procedures are completed. We are sure that this machine will prove to be of a great benefit to us.
CAMPS
On 16th Feb, 2006 MMKCMT conducted a Paediatric Camp at the RHC. About 40 children benefited from the services of the visiting paediatrician.
33 patients with eye ailments were seen and 10 of them operated for Cataracts.
Vascular Diseases Project
With an aim at finding out the incidence/prevalence of Hypertension, Diabetes and IHD amongst the rural poor, the Health centre in collaboration with Monash University of Australia, has just started a one year epidemiological survey, covering a population of 5000.
A Closing Message
We would like to take this opportunity to thank one and all for their support to the Rural Health Centre.
A full list of patients who have been treated at Tertiary Care Centres will be put up on the blogspot at the soonest.
We look forward to your continuing support in the years to come. Please look at www.rvrhc.blogspot.com for our funding requirements.
Kartik and Kamakshi
April 2006
rvsrhc@yahoo.co.in www.rvrhc.blogspot.com www.rishivalley.org
(08571) 280573/280850/280622/280582
Subscribe to:
Posts (Atom)